
Introduction
The American Urological Association has published guidelines for the surgical management of female stress urinary incontinence (1). According to these guidelines, the objective demonstration of stress urinary incontinence should be documented prior to initiating surgical therapy. This can be accomplished with physical examination (filling the bladder and observing stress incontinence with cough or Valsalva maneuver) or with urodynamic testing. This section reviews the various urodynamic techniques used to assess the presence and severity of female stress urinary incontinence.
Leak-Point Pressures
Leak-point pressures are an integral part of urodynamic testing. To understand the utility of leak-point pressures (LPPs) in the evaluation and management of the stress incontinent patient, it is critical to define our terms and the clinical situations to which they apply. There is considerable confusion because there are two main LPPs, and they are known by several names; in fact they are used in different clinical settings.
Detrusor Leak-Point Pressure
Detrusor leak-point pressure (DLPP), also referred to as bladder leak-point pressure, is not a measure of stress urinary incontinence (SUI). However, it is often confused with other LPP measurements used to assess SUI, so a brief review is pertinent. DLPP refers to the lowest measured value of bladder pressure at which urine leakage is noted without detrusor contraction or increases in abdominal pressure. In other words, DLPP is the bladder pressure required to overcome fixed urethral resistance during passive bladder filling in urodynamic testing, and it is marked by leakage.
DLPP was first described in a study of myelodysplastic children; it was noted that children with higher DLPPs (>40 cm H2O) developed upper tract damage; those with lower DLPPs did not (24). Ultimately, DLPP reflects urethral resistance and bladder compliance (C = ∆V/∆P). Whether a patient’s DLPP is high because of excess urethral resistance or low compliance, the end result is a high-pressure system that is at risk for upper tract damage as the increasing bladder pressure overcomes the ureteral expulsive pressure and reflux ensues. DLPP is useful in the evaluation and management of neurogenic bladders in relation to the storage and compliance as a predictor of upper tract health. However, it is not applicable for the assessment of SUI.
{embed=“ref/stat-menu-urodynamic-evaluation”}
Abdominal Leak-Point Pressure (Valsalva Leak-Point Pressure)
Abdominal leak-point pressure is the lowest bladder pressure at which leakage occurs with stress (Valsalva or cough) without detrusor contraction. This measurement is commonly referred to as the Valsalva leak-point pressure (VLPP) but is also known as stress leak-point pressure or cough leak-point pressure (CLPP) depending on the source of increased intraabdominal pressure. For the purposes of this section, we use VLPP because Valsalva is the most common source of stress in urodynamic testing.
Conceptually, VLPP is a dynamic test that reflects the urethral resistance by measuring the intraabdominal pressure that is sufficient to drive urine across the urethral unit.
Stratification of severity and type of stress incontinence based on VLPP measurements are described in the section on interpretation.
{pagebreak}
Techniques
The initial description of the VLPP measurement by McGuire et al. utilized a 10-French triple-lumen pressure-transducing catheter to fill the bladder with contrast to 150 cc with the patient in the upright position. A Valsalva maneuver was performed, and the leak point was defined as the pressure at which contrast was seen to pass through the bladder neck on fluoroscopy (Fig. 1) (2). Numerous subsequent studies have been published using variations of this technique, which has led to difficulty in interpretation of the VLPP measurements and clinical application across studies.
In general, there are six components of VLPP testing that affect the outcome: patient position, catheter size, transducer zeroing, bladder volume, method of leakage observation, and type of stress used to generate increased intraabdominal pressure. It is important to recognize that using absolute numbers for diagnosis is problematic, and caution must be taken to recognize the parameters that are used for interpretation.
PATIENT POSITION
VLPP was originally described with patients in the upright position, although several authors have used the sitting position. One study reported that CLPP measurements were not affected by patient positioning, and the authors recommended utilizing the positioning that best fits the equipment and patient preference (3).
CATHETER SIZE
VLPP has been described with 3-, 8-, and 10- French catheters. It has been demonstrated that larger catheter size results in higher VLPP, possibly because of mild obstruction from the larger catheters (4). At present, there is no standardized catheter size, and the choice is based on practitioner preference.
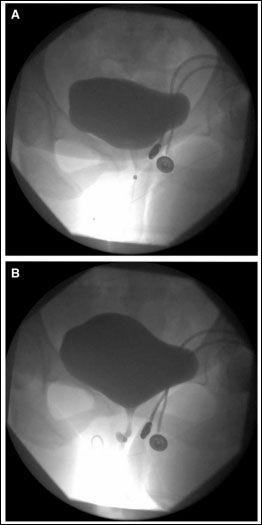
Fig. 1. (A; top) and (B; bottom) correspond to the indicated locations on the urodynamic tracing in
Figure 2. With Valsalva maneuver, contrast is seen to pass through the bladder neck (bottom image).
TRANSDUCER ZEROING
VLPP measurements can be zeroed to the patient or to atmospheric pressure. The original description of VLPP measurements to diagnose the types of stress incontinence was zeroed to atmospheric pressure.
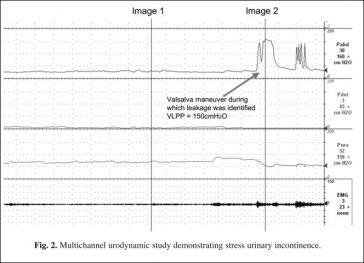
Fig. 2. Multichannel urodynamic study demonstrating stress urinary incontinence.
BLADDER VOLUME
McGuire et al. first described VLPP at a bladder volume of 150 mL (2). Later studies used 250-mL volumes; others have recommended utilizing near-capacity or capacity volumes by data obtained from voiding diaries. Notably, larger volumes have been associated with lower VLPP measurements. Therefore, if leakage is not observed at lower volumes, the bladder can be filled to near capacity, and repeat testing can be performed to see if leakage can be provoked.
{pagebreak}
Method of Observation of Leakage
Leakage can be observed via patient report, direct observation, or fluoroscopy.
Fluoroscopy is the most definitive way to measure leakage objectively, although it adds expense to the exam and is not always readily available. When possible, it should be part of the urodynamic assessment.
TYPE OF STRESS
Stress may be induced by Valsalva or cough. There is discussion in the literature regarding the different effects of the two mechanisms on intra-abdominal pressure.
Some authors have noted that CLPPs are higher than VLPPs. This is thought to be because of reflex contraction of the urethral mechanism during the transient cough, which is not observed during the slow progressive stress of a Valsalva maneuver.
Most urodynamicists would start with VLPP measurement and if negative proceed to CLPP measurements.
Interpretation
The utility of VLPP lies in its potential to quantify the severity of stress incontinence.
Studies have shown that VLPP above 120 cm H2O are typically consistent with type I stress incontinence (urethral hypermobility <2.0 cm); VLPPs between 60 and 120 cm H2O are found with type II stress incontinence (urethral hypermobility >2.0 cm), and those patients with VLPPs below 60 cm H2O commonly demonstrated type III stress incontinence (intrinsic sphincter deficiency). Although this is an attractive algorithm and would apparently lend itself to the determination of appropriate treatment (suspension vs sling vs bulking agents), the variations in technique have a great impact on the results of a given VLPP measurement. Therefore, comparison is difficult across centers and even practitioners.
At present, measurement of the VLPP is useful in characterizing a specific patient’s urethral resistance. If a practitioner utilizes the same techniques with every patient, the practitioner may use the experience to help stratify patients and determine the best treatment option. It is not possible to generalize the measurements of VLPP across patients in different study conditions; therefore, unless universal techniques are adopted and carefully studied, the primary usefulness of VLPP will remain in the hands of individual urologists to interpret.
——
Kelly M. Maxwell, MD, and J. Quentin Clemens, MD, MSCI
——
{embed=“ref/2”}