
A working knowledge of the embryology of the genitourinary tract provides the basis for understanding the structural anomalies encountered in paediatric urological practice. Although this section will concentrate predominantly on the clinical aspects of embryology of the genitourinary tract it will also touch on some of the relevant basic science and summarise developments in the rapidly advancing field of developmental biology.
Genetic basis of genitourinary tract malformations
Chromosomal abnormalities
The nuclear DNA present in the normal human somatic cell is represented by 23 pairs of chromosomes: 22 pairs of autosomes and one pair of sex chromosomes, a karyotype expressed as 46XY (male) or 46XX (female).
Following the sequence of two meiotic divisions during gametogenesis each spermatazoon or oocyte carries only one unpaired copy of each autosome and one sex chromo-ome – either X or Y. Fusion of the nuclear DNA of the gametes at the time of fertilisation imparts the normal diploid status to the fertilised zygote.
Structural chromosomal abnormalities occur either during the formation of the gametes (gametogenesis) or during the first few cell divisions of the fertilised zygote. Examination of spontaneously aborted embryos reveals a high percentage of profound chromosomal abnormalities inconsistent with survival of the embryo. The most serious chromosomal abnormalities compatible with survival to term are trisomy 21 – Down’s syndrome (47XX or 47XY) – and trisomies 13 and 18.
Trisomies result from the failure of a pair of chromosomes to separate fully during gametogenesis, with the result that an additional copy of a chromosome or fragment of chromosome becomes incorporated into the nucleus of a gamete (usually by a process termed translocation or non-disjunction).
The converse of the process, which gives rise to trisomic states, also results in the formation of a gamete that is lacking a copy of a particular chromosome. The zygote formed by fertilisation will therefore have only one copy of this chromosome – termed monosomy. Complete autosomal monosomic states are uniformly lethal but some partial monosomies created by deletion of part of a chromosome are compatible with survival and are associated with specific syndromes.
Deletion of a particular portion of chromosome 11 has been implicated in the aetiology of some Wilms’ tumours.
A similar process of faulty separation affecting the sex chromosomes is encountered in, for example, Klinefelter’s syndrome (47XXY) or Turner syndrome (45X). Monosomic forms (45X) account for approximately 50% of cases of Turner syndrome, mosaicism (45X/46XX ) is present in approximately 30% of cases while a structural deletion on one of the X chromosomes accounts for approximately 20%. Abnormalities of the sex chromosomes often occur in mosaic form, mosaicism being defined as the presence of two chromosomally distinct cell lines derived from the same zygote. In addition to translocation and non-disjunction, structural defects involving identifiable segments of chromosomes include deletion, inversion, duplication and substitution.
The genetic imbalance arising from structural chromosomal abnormalities is expressed as profound disturbances of embryological development across a number of systems, including the genitourinary tract (Table 1.1).
Gene mutations occur in structurally intact chromosomes at the level of the nucleotides comprising the individual genes. Such mutations are not visible on microscopy but are amenable to study by techniques such as PCR (polymerase chain reaction) and FISH (fluorescent in situ hybridisation). The role of individual genes can be elucidated by studying the effects of so-called ‘knock out’ deletion in transgenic mice.
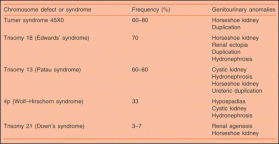
Table1.1 – Chromosome defects associated with urinary tract anomalies
Specific gene mutations have been identified in a number of inherited conditions affecting the genitourinary tract, e.g. autosomal dominant polycystic kidney disease, X-linked Kallmann’s syndrome and renal coloboma syndrome (mutation of the PAX2 gene encoding for a transcription factor expressed during development of the eye and urinary tract).
However, the majority of the congenital anomalies encountered in paediatric urology do not have such a clearly defined genetic basis. They either arise sporadically or are inherited as autosomal dominant traits with variable expression and penetrance. Conditions such as vesicoureteric reflux, upper tract duplication, hypospadias, etc., which exhibit a familial tendency are generally believed to represent the interaction of multiple genes, rather than a single gene mutation.
The extent to which external factors in the fetal or the wider environment influence the expression of genes involved in regulating the development of the genitourinary tract is poorly understood. However, it is known, for example, that gene expression and regulation within the differentiating fetal kidney is markedly affected by early urinary tract obstruction.
——
David FM Thomas FRCP FRCPCH FRCS
St James’s University Hospital
Leeds, UK
Patrick G Duffy MB BCH BAO FRCS(I) FEBU
Great Ormond Street
Hospital for Sick Children
London, UK
Anthony MK Rickwood MA FRCS
Formerly of Royal Liverpool
Hospital for Sick Children
Liverpool, UK
